
Home
BCBS Billing Specialists

Blue Cross Blue Shield Billing Services
Blue Cross Blue Shield is a federation of 34 independent member plans, each with its own fee schedules, authorization requirements and submission rules. Revix MD manages that plan-level complexity so your revenue cycle stays consistent and your collections stay accurate, regardless of which Blue plan your patients carry.



Why BCBS Billing Is Different
Blue Cross Blue Shield Billing Carries Risks Most Practices Underestimate
BCBS is not a single insurer. It’s a network of 34 independent member plans, each enforcing its own CPT bundling rules, modifier policies, fee schedules, provider credentialing requirements, and prior authorization thresholds. A claim that pays cleanly under BCBS of Texas can be denied under BCBS of Illinois for the identical procedure, which is where denial management services step in to identify root causes and prevent repeat issues.
That fragmentation costs practices money every day. Mismatched plan codes, outdated EDI enrollment, stale coordination of benefits data or a single missed authorization can push a clean encounter into aging A/R — or trigger a denial that costs three times as much to resolve as it did to file. These are not edge cases. They are the operational patterns we see in almost every practice that comes to us.
BCBS Risk Factors
Where BCBS Complexity Creates Revenue Exposure
These are not edge cases. They are the operational patterns we see in almost every practice that comes to us.
Plan Fragmentation
Each of the 34 BCBS regional plans enforces different CPT bundling logic, modifier requirements and authorization thresholds. Generic billing fails at the plan level.
BlueCard Routing
Wrong alpha prefix or host-plan submission path delays payment and generates avoidable rejections on inter-plan claims.
Prior Auth Complexity
BCBS plans have tightened prior authorization significantly. Missing or expired auths now rank among the top denial drivers across specialties.
FEP Billing Rules
Federal Employee Program claims follow distinct filing windows, medical necessity criteria, and COB rules. Treating FEP like standard BCBS is costly.
Underpayment Exposure
BCBS remittances frequently reflect payments below contracted rates. Most teams lack bandwidth to systematically audit EOBs against contract terms.
No Surprises Act
OON BCBS claims carry strict balance billing constraints and dispute resolution timelines. Precise documentation and timely IDR filings are required.
Credentialing & EDI
Lapses in credentialing with the relevant BCBS member plan or outdated EDI enrollment can produce months of retrospective denials.
Medical Policy Cycles
Each BCBS plan updates LCDs, NCDs, and billing policies on its own schedule. Staying current requires active payer monitoring, not reactive catch-up.
Our Services
Full-Cycle BCBS Billing: Front-End Through Final Payment
Effective Blue Cross medical claims processing requires accuracy at every point in the revenue cycle, not just claim submission.
Front-End Services
Insurance Eligibility & Benefits Verification
Real-time eligibility checks against the patient’s active BCBS plan before every encounter, including deductibles, co-pays, out-of-pocket balances and benefit limitations backed by eligibility verification services that confirm coverage before care is delivered.
BCBS Prior Authorization Management
We identify authorization requirements by plan and procedure, submit requests to the correct BCBS entity, track pending decisions and flag expiring auths before appointments occur.
Patient Demographics Review
Member IDs, group numbers, alpha prefixes and subscriber relationships are validated at registration. Inaccurate demographics are among the most preventable sources of claim errors.
Coordination of Benefits (COB)
When BCBS is one of multiple payers, we establish primary vs. secondary payer status before submission — preventing sequencing errors and duplicate billing flags.
Accurate Charge Entry
Charges entered against BCBS plan-specific fee schedules and modifier rules, with medical coding review to maximize compliant reimbursement from the first submission.
Back-End Services
Claims Processing & Scrubbing
Every claim passes automated and manual scrubbing before EDI submission — with real-time tracking of acknowledgment, payer acceptance and pre adjudication edits.
Denial Management & Appeals
Denials categorized by type (CO-4, CO-197, PR-204), root-caused to the originating workflow failure, and appealed with supporting clinical and administrative documentation.
Payment Posting & Underpayment Recovery
EOBs and ERAs posted against expected contracted rates for each BCBS plan. Discrepancies trigger immediate underpayment recovery workflows with systematic audits.
A/R Follow-Up & Recovery
Accounts receivable worked by aging bucket and claim status — preventing BCBS timely filing deadlines from closing valid receivables before they’re collected.
Reporting & Analytics
Monthly dashboards surface denial root-cause breakdowns by BCBS plan, first-pass rates, A/R aging by payer, reimbursement trends, and authorization approval rates.
Plan-Level Intelligence
How We Handle BCBS Plan Differences
Our billing team maintains plan-level documentation for each BCBS regional entity, updated through active payer monitoring — not reactive catch-up after claims have already started denying.
BlueCard Program Routing
We manage routing verification pre-submission using the member’s alpha prefix to prevent inter-plan processing errors.
FEP Billing Requirements
Our billers are trained on FEP- specific timely filing windows, medical necessity standards, and COB rules — separate from commercial BCBS policies.
Inter-Plan Telehealth
Telehealth claims crossing state-plan boundaries involve coverage determinations and modifier requirements that vary by originating and distant site plan.
LCD/NCD Monitoring
When a BCBS plan updates its medical policies or fee schedules, we adjust claim logic before it affects reimbursement.
Credentialing Tracking
We track credentialing status across every plan variant relevant to your patient population and flag gaps before they produce retrospective denials.
Plan-Specific Modifiers
Modifier requirements for bilateral procedures and assistants-at-surgery vary by regional plan. We apply plan- specific logic at charge entry.
Denial Workflow
BCBS Denials Start to Resolution
We manage denials” is not a methodology. Here is how our BCBS denial management workflow actually operates.
Denial Category
Common Codes
Root Cause
Resolution Path
Medical Necessity
CO-50, CO 57, PR-204
Missing clinical documentation; diagnosis-procedure mismatch
Clinical documentation request, formal appeal; peer-to-peer review when warranted
Authorization / Referral
CO-15, CO-197
Missing prior auth, expired auth, or service outside scope
Retroactive auth request; appeal with clinical rationale; corrected claim
Bundling / Unbundling
CO-4, CO-97
Plan-specific CPT bundling rules differ from standard CCI
Modifier review; plan-level bundling policy review; appeal with operative report
Eligibility / Coverage
CO-27, CO-29
Inactive member ID, COB error, or OON filing without notice
Eligibility re-verification; COB correction; No Surprises Act dispute filing
Timely Filing
CO-29
Claim submitted outside the BCBS plan’s filing window
Documentation of original timely submission; appeal with
proof of filing
Credentialing / Network
CO-24, CO-242
Provider not credentialed with specific member plan at time of service
Credentialing audit; retroactive enrollment request; appeal with documentation
Appeal Escalation Path: Corrected claim resubmission → First-level reconsideration → Formal written appeal → Peer-to-peer review (clinical) → External review or IDR where applicable under plan terms and No Surprises Act provisions.
Technology & Automation
The Infrastructure Behind Our BCBS Clean Claim Rates
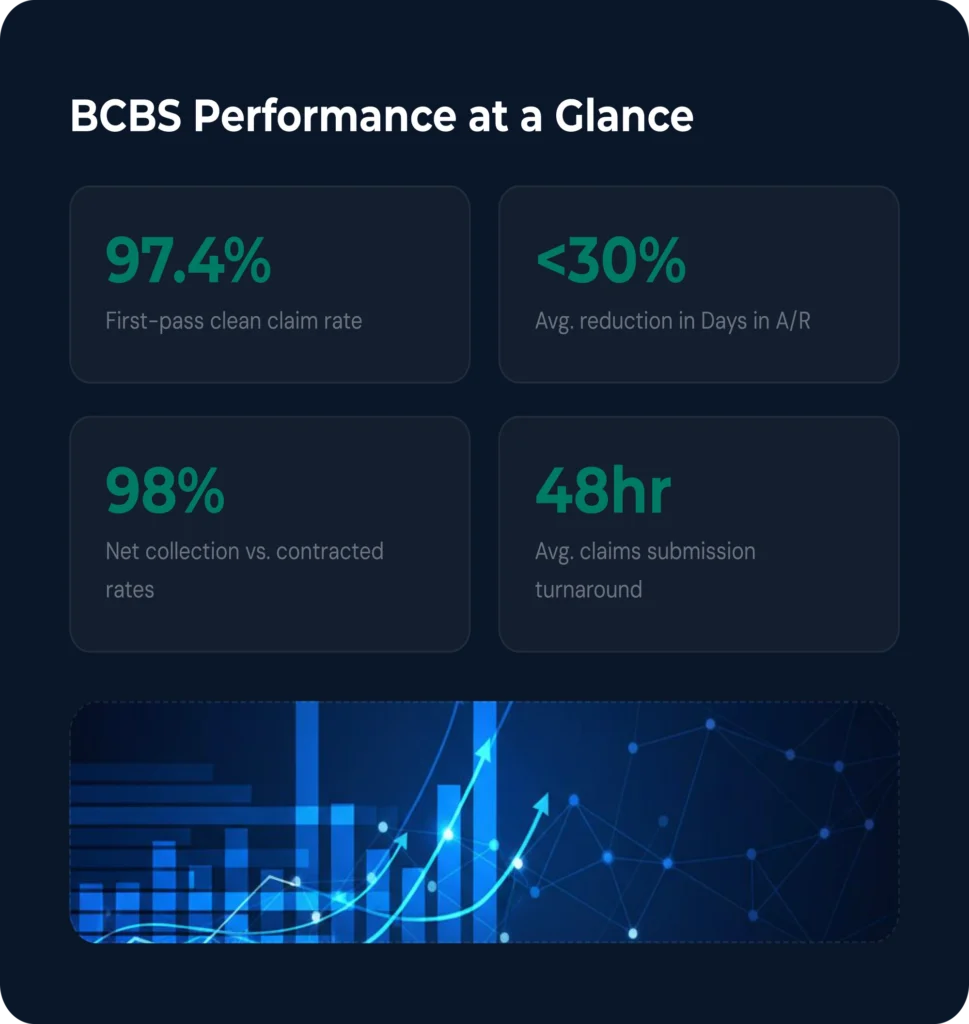
The workflows that produce a 97.4% first-pass clean claim rate are supported by purpose-built technology at every stage.
Rules-Engine Claim Scrubbing
BCBS-configured rules engine flags plan-specific bundling violations, modifier mismatches, and missing auth references before submission.
Automated Eligibility APIs
Real-time eligibility checks run against BCBS plan data via API — returning active coverage status, benefit details, and COB flags without manual lookups.
Denial Pattern Analytics
Denial root-cause data tracked by BCBS plan, denial code, and provider — surfacing systematic patterns that warrant workflow corrections.
Payer Policy Monitoring
Monitored feed of BCBS medical policy updates, LCD/NCD changes and fee schedule revisions — claim logic updated proactively when policies shift.
ERA / EOB Reconciliation
Electronic Remittance Advice reconciled against contracted rates at the line-item level. Underpayments flagged automatically and routed to recovery.
EHR-Integrated Charge Retrieval
Charges pull directly from your EHR or PM system via API, HL7/FHIR feed, or structured encounter import — eliminating manual re-entry errors.
We Work Inside Your Existing EHR
Our team handles charge retrieval, claim creation, payer response processing and reporting without asking you to change platforms.
KareoAthenahealtheClinicalWorksAdvancedMDDrChronoEpicCernerNextGen
Getting Started
What Transitioning Your BCBS Billing Looks Like
Most practices are fully onboarded within 10–15 business days. Here is how the transition works — and what we manage so your billing cycle isn’t disrupted.
Credentialing & Contract Audit
We review your credentialing status with each relevant BCBS member plan and flag any enrollment gaps or contract discrepancies before they become billing problems.
EDI Enrollment Verification
EDI enrollment is confirmed or updated for each BCBS plan entity in your payer mix. We don’t assume existing enrollment is current — we verify it.
EHR Access & Integration
EHR or PM system access is configured for charge retrieval and claim creation. Integration method — API, HL7/FHIR feed or structured import — is established based on your platform.
Test Claim Submission
We run a test submission cycle with sample claims before going live — confirming clearinghouse connections, payer acceptance and reporting feeds are functioning.
Go-Live & Monitoring
Full claim submission begins with parallel monitoring of acknowledgments, payer responses, and ERA/EOB posting during the first billing cycle.
Already Billing BCBS?
Switching From In-House or Another Vendor
The real question is not whether to bill BCBS, but whether the current approach is capturing what is contractually owed.
Common Gaps in In-House BCBS Billing
What Transitions to Revix MD Produce
Transition risk: Patients do not interact with billing operations directly. Payment and billing communications remain consistent through the transition period. Your BCBS contract terms are reviewed before onboarding begins — not assumed.
Specialties Served
Specialty-Specific BCBS Billing Across Practice Types
BCBS billing requirements vary meaningfully by specialty — coding complexity, authorization frequency, and plan-level medical policy scrutiny differ across service lines.
Internal MedicineFamily PracticeCardiologyOrthopedicsMental & Behavioral HealthGastroenterologyNeurologyOncologyPhysical TherapyRadiologyOB-GYNPain ManagementUrgent CarePodiatryMulti-Specialty Groups
What Sets Us Apart
Why Expert BCBS Billing Matters
"
Plan-level documentation, updated actively. Our billers work from maintained, plan-specific documentation — not generic payer rules applied uniformly. Fewer denials from misapplied regional policies.
Plan-Level BCBS Documentation
"
We address root causes at the front end through eligibility verification, authorization tracking, and coding precision. The goal is to shrink your BCBS denial rate at its source — not manage preventable write-offs.
Denial Prevention First
"
You work with a billing specialist who knows your practice, your BCBS payer mix, and your contract terms. When a policy changes or denial pattern emerges, your account manager identifies it first.
Dedicated Account Management
Get a Plan-Level BCBS Billing Assessment
We’ll identify where revenue is slipping — whether that’s denial patterns, underpayment exposure, authorization gaps or plan-specific submission errors — and present a clear recovery plan.
Frequently Asked Questions
Can Revix MD handle billing across multiple BCBS regional plans simultaneously?
Yes. If your patient base spans multiple BCBS regional plans – such as BCBS of Michigan, Anthem BCBS of Ohio, and BCBS of Texas – we manage each plan’s submission requirements, fee schedules and payer portals independently. Your revenue cycle does not have to be restructured around payer geography.
How quickly can you take over an existing practice's BCBS billing?
Most practices are fully onboarded within 10–15 business days. That includes credentialing and EDI enrollment verification, EHR access setup, integration configuration and a test claim submission cycle before go-live. We manage the transition to minimize disruption to your billing cycle.
How do you handle my specific BCBS contract terms?
Before onboarding begins, we review your BCBS contract terms – fee schedules, carve-outs, and any plan-specific billing requirements and build those into our claim scrubbing and payment posting workflows. Contracted rates are the benchmark for every ERA reconciliation we run.
Do you handle prior authorization for BCBS plans?
Yes – BCBS prior authorization management is a core part of our front-end services. We identify which procedures and diagnoses require authorization under each BCBS plan, submit requests to the correct plan entity, track pending decisions and notify your clinical team of approvals or medical necessity disputes before the patient’s appointment.
What happens when a BCBS claim is denied?
Denials enter our denial management workflow immediately. We categorize the denial by type (CO-4, CO-197, PR-204 and others), determine whether it requires a corrected claim, additional documentation or a formal appeal, and execute accordingly. For medical necessity denials, we coordinate peer-to-peer review requests with your providers. Appeal escalation follows a defined path: corrected claim → first-level reconsideration → formal written appeal → peer-to-peer or external review where applicable.
Will my patients notice any change during the transition?
No. Patients do not interact with billing operations directly. Payment workflows and any patient-facing billing communications remain consistent through the transition. Our onboarding process is designed to be invisible to your patients – and to your clinical staff beyond an initial workflow orientation.
Is Revix MD HIPAA compliant?
Yes. All billing operations, data handling, and communication channels comply with HIPAA Privacy and Security Rules. PHI is encrypted in transit and at rest and system access is role-restricted by function. We execute a Business Associate Agreement with every client practice before any PHI is accessed or transferred.